

 PDF下载 ( 26227 KB)

滋养层来源的间充质干细胞对自身免疫性肝炎小鼠模型肝损伤的保护作用及其机制
DOI: 10.12449/JCH260916
Protective effect and mechanism of trophoblast-derived mesenchymal stem cells against liver injury in a mouse model of autoimmune hepatitis
-
摘要:
目的 探讨滋养层来源的间充质干细胞(T-MSC)对刀豆蛋白A(Con A)诱导小鼠免疫性肝损伤的影响,并分析其与炎症反应变化的关系。 方法 采用形态学观察、流式细胞术及三系分化实验对T-MSC进行生物学特征鉴定。预实验设置磷酸盐缓冲溶液组、T-MSC单独给药组及Con A 10、15、20 mg/kg梯度组,用于评价T-MSC单独给药的肝功能安全性并筛选适宜造模剂量。正式实验设健康对照组(HC组)、Con A组和Con A+T-MSC组,每组5只小鼠。采用尾静脉注射Con A(经筛选,适宜的造模剂量为15 mg/kg)建立小鼠免疫性肝损伤模型,T-MSC单独给药组于建模后3 h经尾静脉输注T-MSC 1×10⁶个/只,12 h后取材。检测血清丙氨酸氨基转移酶(ALT)、天冬氨酸氨基转移酶(AST)和乳酸脱氢酶(LDH)水平;观察肝组织病理学改变,评估Ishak炎症活动评分及炎症坏死面积;测定血清炎症因子水平;并结合转录组测序、免疫荧光和蛋白质印迹法(Western Blot)分析肝组织炎症相关分子变化。采用Shapiro-Wilk检验评估计量资料的正态性,并进行方差齐性检验。符合正态分布且方差齐的计量资料多组间比较采用单因素方差分析,进一步两两比较采用Tukey法;不符合正态分布或方差不齐的计量资料多组间比较采用Kruskal-Wallis H检验,进一步两两比较采用Wilcoxon秩合检验。 结果 T-MSC呈长梭形、成纤维样贴壁生长,具成骨、成软骨和成脂分化能力。流式细胞术显示,T-MSC高表达分化簇(CD)90、CD105和CD73,阳性率分别为96.8%、99.0%和99.9%,而CD31、人类白细胞抗原DR、CD45和CD34表达较低或不表达,阳性率分别为0.120%、0、0.061%和0。T-MSC单独给药未见ALT、AST和LDH水平明显异常。Con A 10、15和20 mg/kg均可导致血清肝脏生化指标水平升高,且整体呈剂量依赖性变化,20 mg/kg组出现小鼠死亡。正式实验中,与HC组比较,Con A组ALT、AST和LDH水平均显著升高(P值均<0.01);经T-MSC干预后,上述指标均较Con A组显著下降(P值均<0.01)。苏木精-伊红染色结果显示,Con A组肝组织结构紊乱,伴明显炎性细胞浸润及灶片状坏死,T-MSC干预后上述病理改变减轻。Con A组Ishak评分及炎症坏死面积占比均较HC组显著升高(P值均<0.001),T-MSC干预后均较Con A组显著降低(P值均<0.01)。酶联免疫吸附测定结果显示,与HC组比较,Con A组血清白细胞介素(IL)21、IL-1β、IL-2、IL-17A和肿瘤坏死因子α(TNF-α)水平均显著升高(P值均<0.05);T-MSC干预后均较Con A组显著下降(P值均<0.05),其中IL-21、IL-1β、IL-17A和TNF-α水平与HC组比较差异均无统计学意义(P值均>0.05);而IL-2水平虽显著下降,但仍高于HC组(P=0.001)。与之相反,IL-10在Con A组较HC组显著升高(P<0.05),T-MSC干预后进一步升高(P<0.05)。转录组分析显示,T-MSC干预后Ccl2、Cxcl10、Il-21、Il-6等炎症及趋化因子相关基因整体表达下调,TNF、IL-17、核因子κB及Janus激酶-信号转导与转录激活因子等炎症相关通路受抑。免疫荧光定量结果显示,Con A组肝组织IL-21表达较HC组显著升高(P<0.001),T-MSC干预后较Con A组显著下降(P<0.001),Western Blot结果与之一致。 结论 T-MSC可减轻Con A诱导的小鼠免疫性肝损伤,表现为血清肝脏生化指标改善、组织学损伤减轻及炎症相关分子整体表达下调。T-MSC在该模型中具有较明确的整体抗炎和免疫调节作用;其中IL-21在炎症反应变化中较为突出,可作为进一步观察的候选分子之一。 Abstract:Objective To investigate the effect of trophoblast-derived mesenchymal stem cell (T-MSC) on concanavalin A (Con A)-induced immune-mediated liver injury in mice, as well as its association with the changes in inflammatory response. Methods Morphological assessment, flow cytometry, and tri-lineage differentiation assay were used to observe the biological characteristics of T-MSC. In the pilot experiment, mice were divided into PBS group, T-MSC monotherapy group, and Con A groups at a concentration of 10, 15, or 20 mg/kg to evaluate the safety of T-MSC monotherapy on liver function and determine the appropriate dose for modeling. In the formal experiment, mice were divided into healthy control group (HC group), Con A group, and Con A+T-MSC group, with 5 mice in each group. The mice were given injection of Con A (15 mg/kg) via the caudal vein to establish a mouse model of immune-mediated liver injury, while the mice in the T-MSC monotherapy group were given transfusion of 1×10⁶ T-MSCs via the caudal vein at 3 hours after modeling, and samples were collected 12 hours later. The serum levels of alanine aminotransferase (ALT), aspartate aminotransferase (AST), and lactate dehydrogenase (LDH) were measured; liver histopathological changes were observed, and Ishak inflammatory activity score and inflammatory necrosis area were assessed; the serum levels of inflammatory cytokines were measured; transcriptome sequencing, immunofluorescence assay, and Western blot were used to measure the changes in inflammation-related molecules in liver tissue. The Shapiro-Wilk test was used to assess the normality of continuous data, and the homogeneity of variance test was also performed; a one-way analysis of variance was used for comparison of normally distributed data with homogeneity of variance between multiple groups, and the Tukey’s post-hoc test was used for further comparison between two groups; the Kruskal-Wallis H test was used for comparison of non-normally distributed data with heterogeneity of variance between multiple groups, and the Wilcoxon test was used for further comparison between two groups. Results T-MSC had a long spindle shape, showed the characteristics of fibroblast-like morphology and adherent growth, and possessed the osteogenic, chondrogenic, and adipogenic differentiation abilities. Flow cytometry showed high expression levels of CD90, CD105, and CD73 in T-MSC, with a positive rate of 96.8%, 99.0%, and 99.9%, respectively, while there was low or no expression of CD31, human leukocyte antigen DR, CD45, and CD34, with a positive rate of 0.120%, 0, 0.061%, and 0, respectively. Administration of T-MSC alone did not cause obvious abnormalities in ALT, AST, or LDH. Con A at the concentrations of 10, 15, and 20 mg/kg all increased the serum levels of biochemical parameters for liver injury in a dose-dependent manner, with mortality observed in the 20 mg/kg group. In the formal experiment, compared with the HC group, the Con A group had significant increases in the serum levels of ALT, AST, and LDH (P<0.01), and after T-MSC treatment, there were significant reductions in these markers compared with the Con A group (P<0.01). HE staining showed that the Con A group had disordered structure of the liver, accompanied by marked inflammatory cell infiltration and focal/patchy necrosis, and these pathological changes were alleviated after T-MSC treatment. Compared with the HC group, the Con A group had significant increases in Ishak score and the percentage of inflammatory necrosis area (P<0.001), while there were significant reductions in these indicators after T-MSC treatment compared with the Con A group (P<0.01). ELISA showed that compared with the HC group, the Con A group had significant increases in the serum levels of interleukin-21 (IL-21), interleukin-1β (IL-1β), interleukin-2 (IL-2), interleukin-17A (IL-17A), and tumor necrosis factor-α (TNF-α) (P<0.05), and there were significant reductions in these markers after T-MSC treatment compared with the Con A group (P<0.05), with no significant differences in IL-21, IL-1β, IL-17A, and TNF-α compared with the HC group (P>0.05); although there was a significant reduction in the level of IL-2, the Con A+T-MSC group still had a significantly higher level of IL-2 than the HC group (P=0.001). In contrast, compared with the HC group, the Con A group had a significant increase in IL-10 (P<0.05), with a further increase after T-MSC treatment (P<0.05). The transcriptome analysis showed that T-MSC treatment downregulated the expression of the inflammation- and chemokine-related genes including Ccl2, Cxcl10, Il-21, and Il-6 and inhibited the inflammation-related pathways such as TNF, IL-17, nuclear factor-κB, and JAK-STAT. Immunofluorescence assay showed that compared with the HC group, the Con A group had a significant increase in the expression of IL-21 in the liver (P<0.001), and there was a significant reduction in IL-21 after T-MSC treatment compared with the Con A group (P<0.001); the results of Western blot showed the same trend. Conclusion T-MSC can alleviate Con A-induced immune-mediated liver injury in mice, as evidenced by the improvement in liver biochemical parameters, the alleviation of histopathological damage, and the overall downregulation of inflammation-related molecules. T-MSC exerts marked anti-inflammatory and immunomodulatory effects in this model, and IL-21 shows a significant change in inflammatory response and can be used as a candidate molecule for further investigation. -
Key words:
- Hepatitis, Autoimmune /
- Mesenchymal Stem Cells /
- Interleukins /
- Concanavalin A /
- Immunomodulation
-
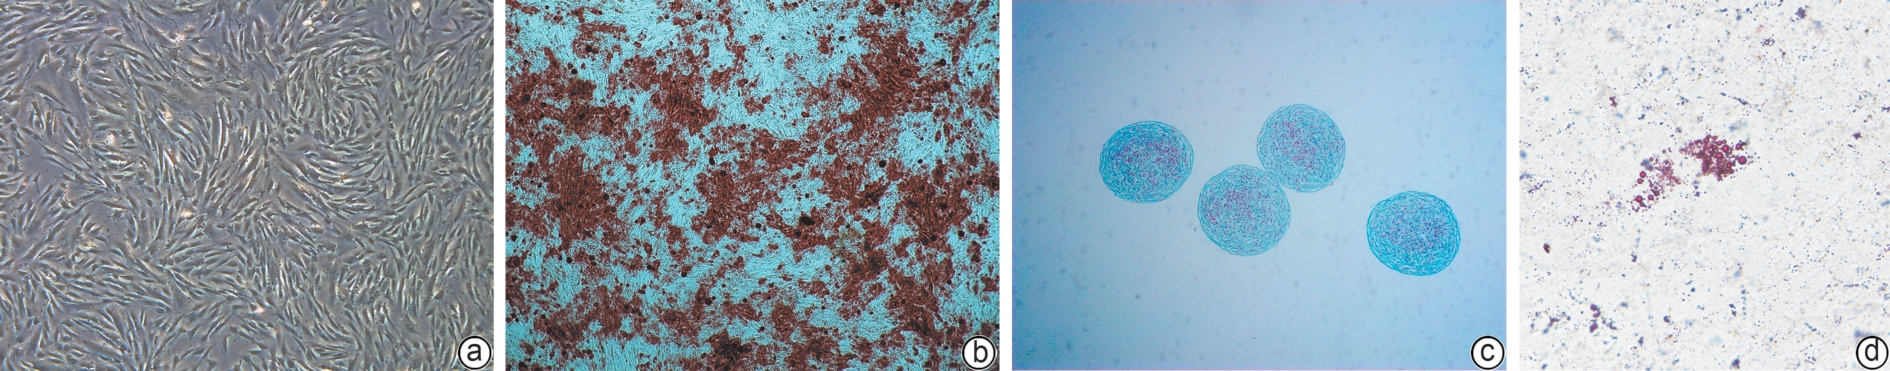
注: a,T-MSC细胞形态(×10);b,成骨分化(茜素红染色,×4);c,成软骨分化(阿利新蓝染色,×4);d,成脂分化(油红O染色,×20)。T-MSC,滋养层来源的间充质干细胞。
图 1 T-MSC的形态及三系分化能力
Figure 1. Morphology and trilineage differentiation of T-MSC
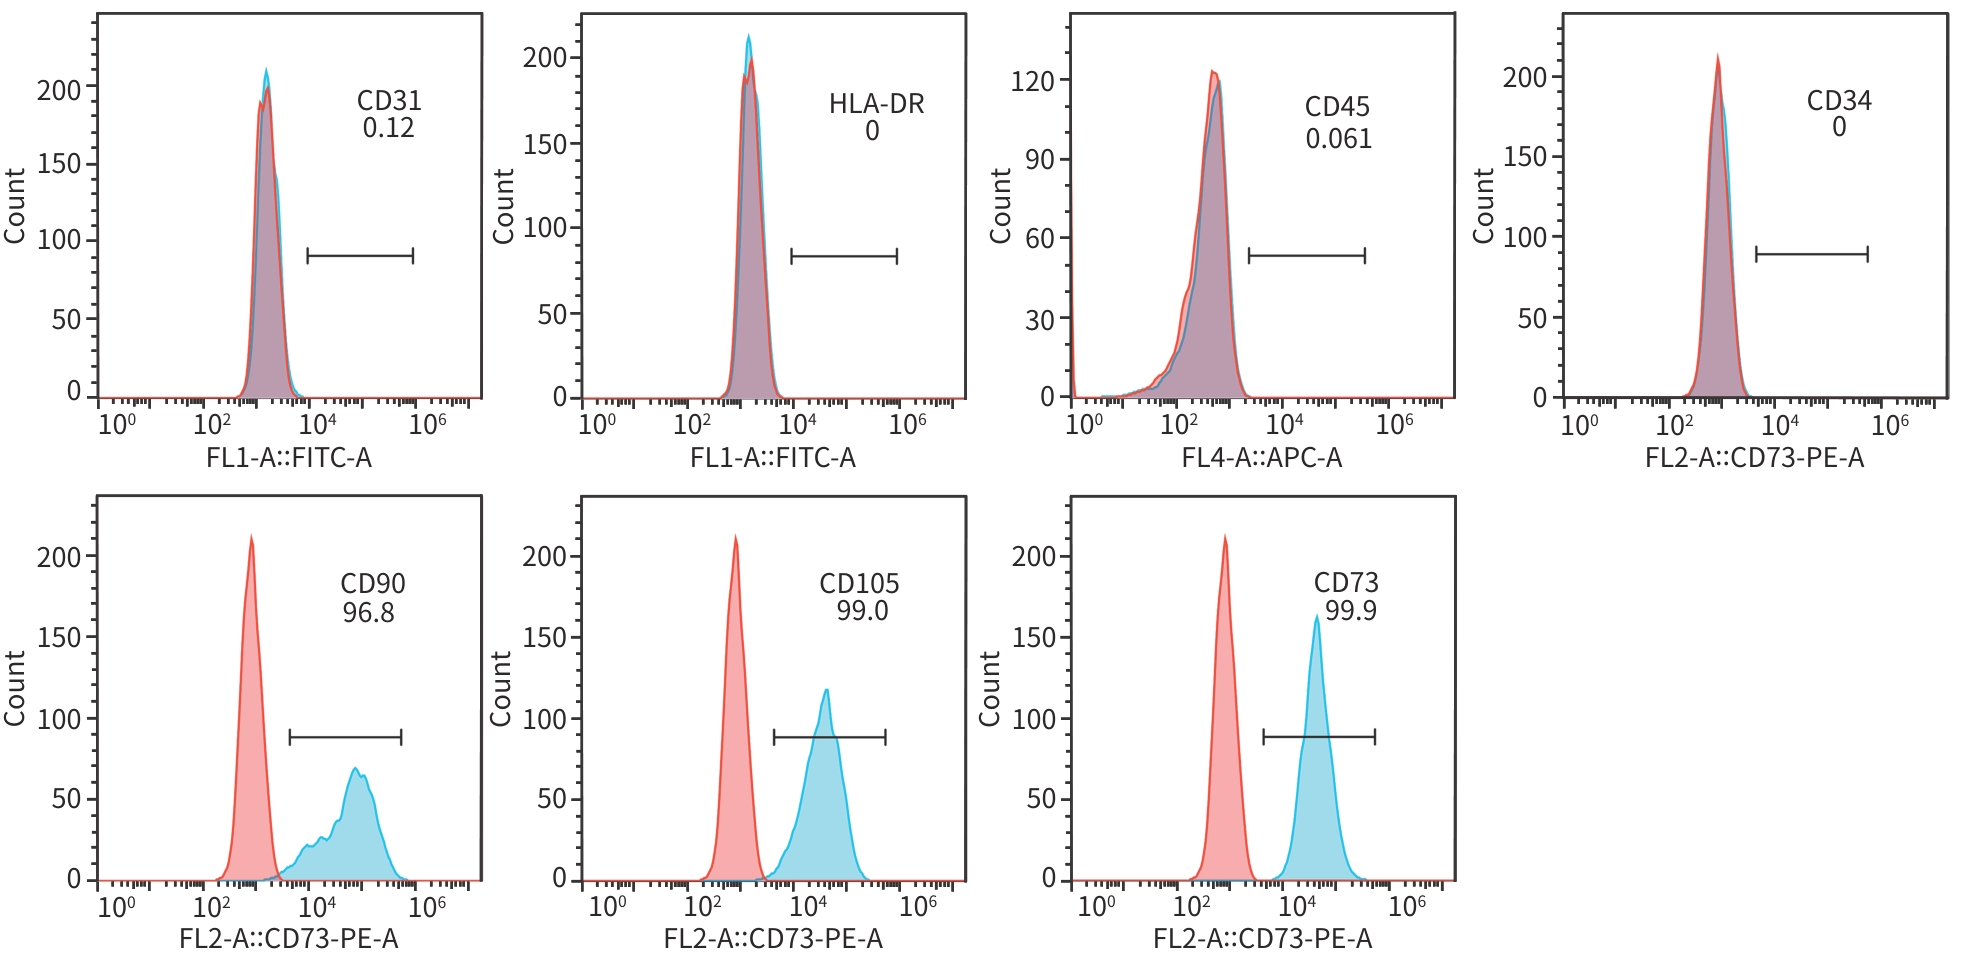
注: CD,分化簇;HLA-DR,人类白细胞抗原DR;T-MSC,滋养层来源的间充质干细胞。
图 2 T-MSC鉴定的流式细胞仪结果
Figure 2. Flow cytometry results of T-MSC identification
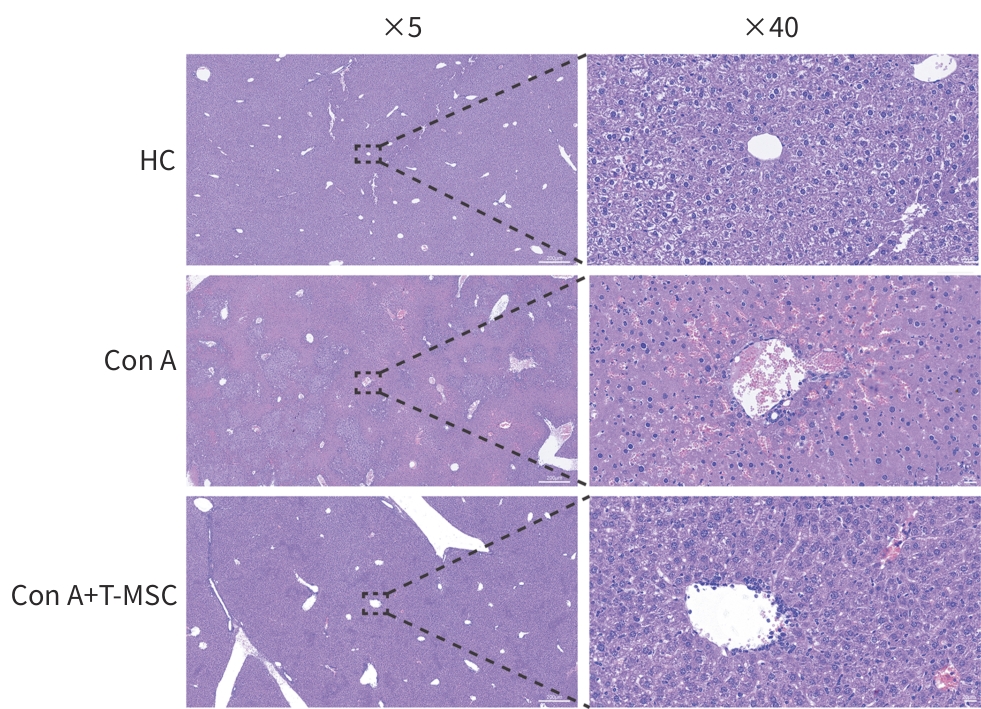
注: HC,健康对照组;Con A,模型组;Con A+T-MSC,治疗组。T-MSC,滋养层来源的间充质干细胞;Con A,刀豆蛋白A。
图 3 T-MSC对Con A诱导小鼠肝组织病理损伤的改善作用(苏木精-伊红染色)
Figure 3. Effects of T-MSC on histopathological liver injury in Con A-treated mice (HE staining)
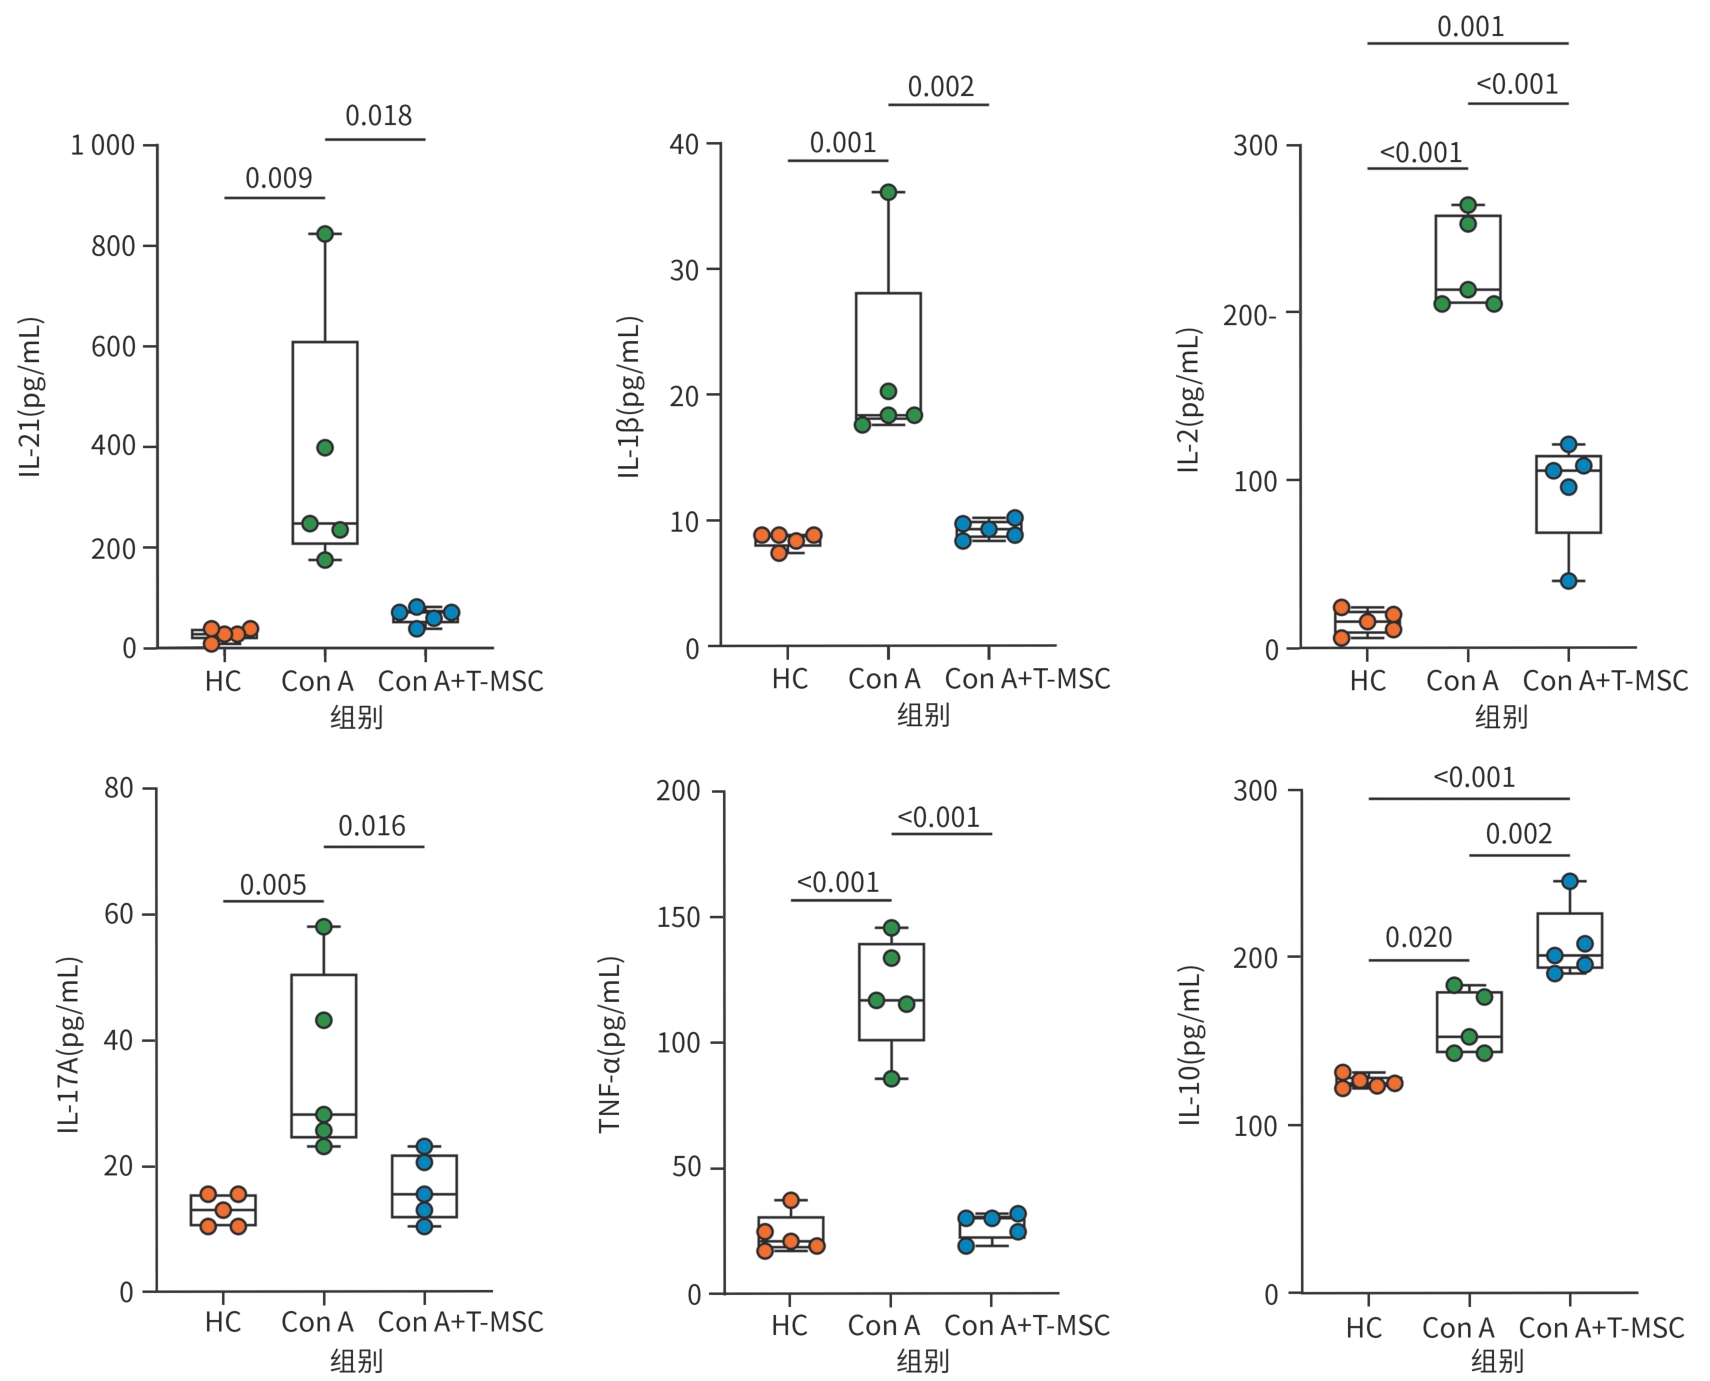
注: HC,健康对照组;Con A,模型组;Con A+T-MSC,治疗组。IL,白细胞介素;TNF-α,肿瘤坏死因子α;T-MSC,滋养层来源的间充质干细胞;Con A,刀豆蛋白A。
图 4 T-MSC 对Con A诱导小鼠血清炎症因子表达的影响
Figure 4. Effects of T-MSC on serum inflammatory cytokine levels in Con A-treated mice
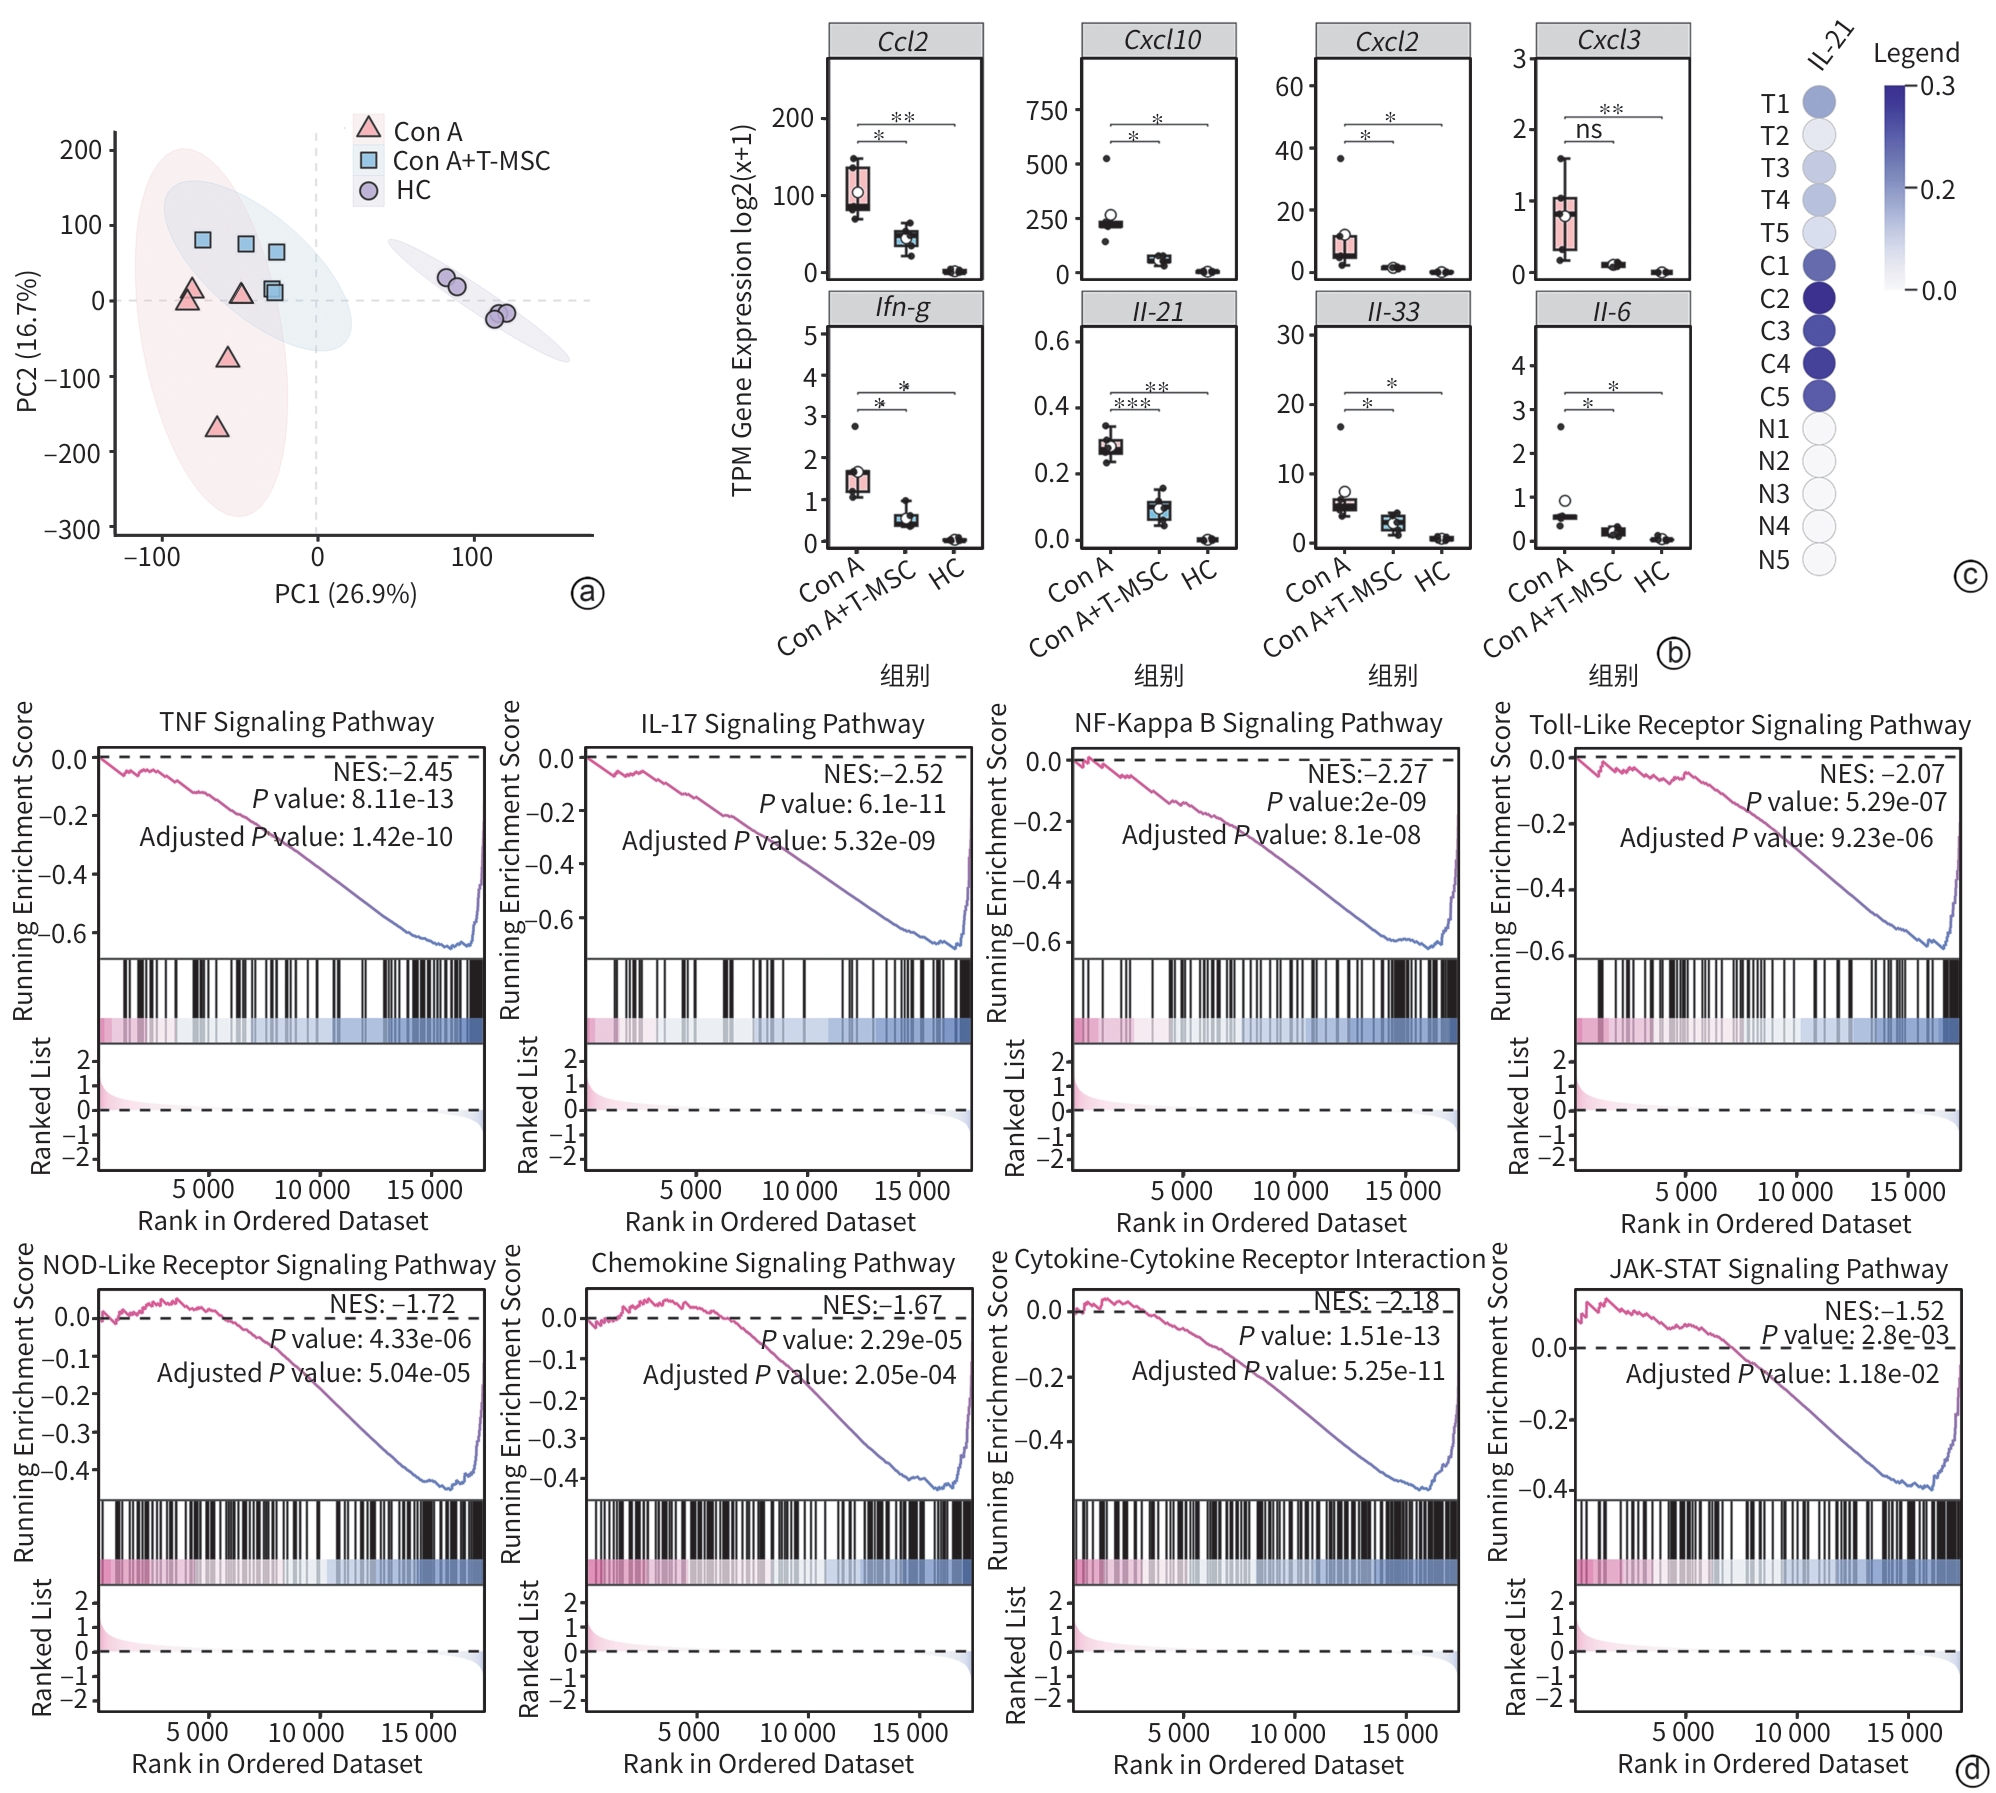
注: a,各组样本主成分分析;b,差异炎症/趋化因子相关基因表达比较;c,各样本Il-21基因表达分布;d,基因集富集分析显示T-MSC干预后炎症相关通路负向富集。T/Con A+T-MSC,治疗组;C/Con A,模型组;N/HC,健康对照组。IL,白细胞介素;T-MSC,滋养层来源的间充质干细胞;Con A,刀豆蛋白A。
图 5 肝组织转录组分析显示T-MSC抑制炎症相关基因表达及通路活化
Figure 5. Transcriptomic analysis of liver tissues showing suppression of inflammatory genes and pathways after T-MSC treatment
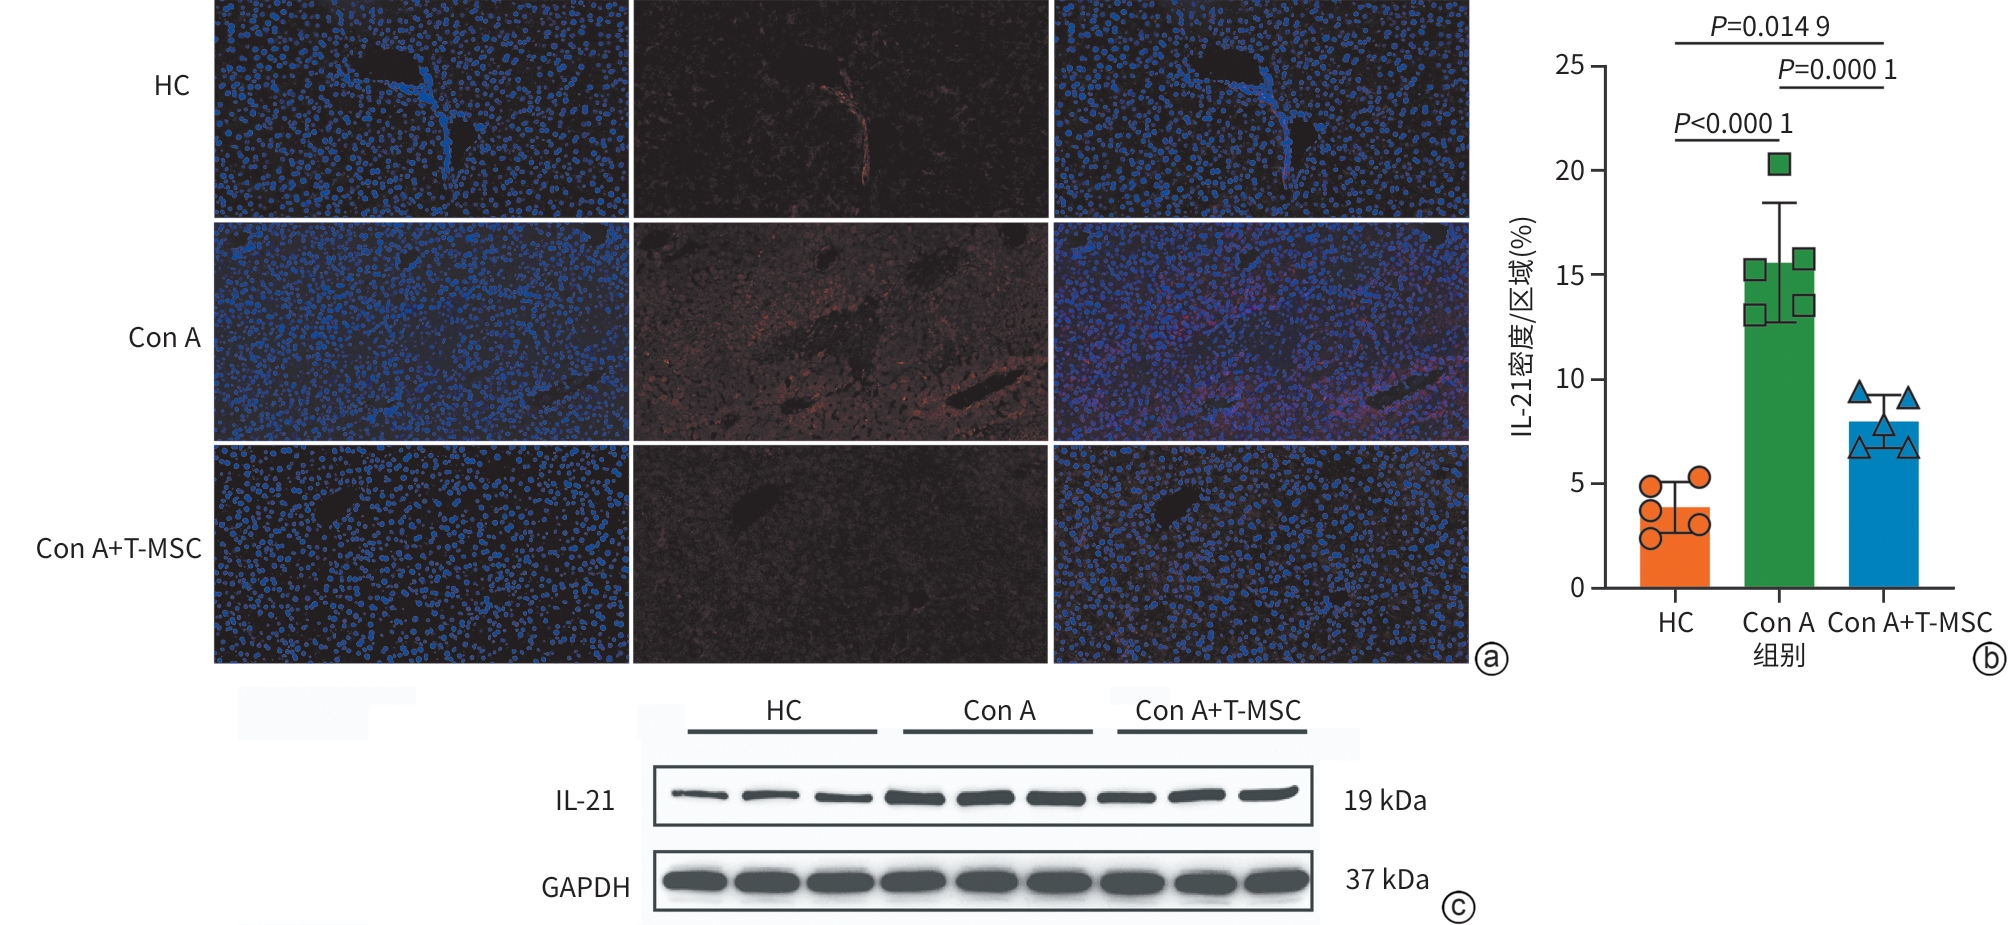
注: a,各组肝组织IL-21免疫荧光染色结果,其中4',6-二脒基-2-苯基吲哚标记细胞核,比例尺=100 μm;b,IL-21荧光密度/区域定量分析;c,Western Blot检测各组肝组织IL-21蛋白表达。HC为健康对照组,Con A为模型组,Con A+T-MSC为治疗组。IL,白细胞介素;T-MSC,滋养层来源的间充质干细胞;Con A,刀豆蛋白A。
图 6 免疫荧光及Western Blot验证T-MSC对肝组织IL-21表达的影响
Figure 6. Immunofluorescence and Western blot validation of IL-21 expression in liver tissues after T-MSC treatment
表 1 T-MSC单独给药及不同Con A剂量对小鼠血清肝功能指标的影响
Table 1. Effects of FMSC monotherapy and different Con A doses on serum liver function indicators in mice
组别 ALT(U/L) AST(U/L) LDH(U/L) PBS组 35.1(26.3~46.8) 78.4(45.7~134.7) 446.9(247.9~805.6) T-MSC组 35.5(27.2~46.4) 106.9(84.6~135.2) 609.7(436.0~852.5) Con A 10 mg/kg组 2 297.8(1 970.6~2 679.4)1)2) 1 772.3(1 512.5~2 076.8)1)2) 7 924.7(6 692.6~9 383.8)1)2) Con A 15 mg/kg组 3 463.4(3 024.4~3 966.0)1)2)3) 2 993.1(1 909.9~4 690.6)1)2) 11 985.9(10 616.1~13 532.5)1)2) Con A 20 mg/kg组 10 433.9(8 666.6~12 561.7)1)2)3)4) 10 031.0(8 188.6~12 288.0)1)2)3)4) 25 332.6(21 322.8~30 096.4)1)2)3)4) F值 1 108.128 232.813 201.218 P值 <0.001 <0.001 <0.001 注:与PBS组比较,1)P<0.05;与T-MSC组比较,2)P<0.05;与Con A 10 mg/kg组比较,3)P<0.05;与Con A 15 mg/kg组比较,4)P<0.05。ALT,丙氨酸氨基转移酶;AST,天冬氨酸氨基转移酶;LDH,乳酸脱氢酶;PBS,磷酸盐缓冲溶液;T-MSC,滋养层来源的间充质干细胞;Con A,刀豆蛋白A。
 下载: 导出CSV
表 2 不同处理组小鼠肝功能及肝组织病理学指标比较
Table 2. Comparison of liver function and pathological indicators of liver tissue in different treatment groups of mice
组别 ALT(U/L) AST(U/L) LDH(U/L) 炎症坏死面积(%) Ishak评分 HC组 33.1(24.0~45.5) 97.8(77.1~124.0) 536.9(370.0~779.1) 0.11(0.00~0.19) 1(0~1) ConA组 3 733.5(1 999.8~6 970.1)1) 2 906.6(1 742.5~4 848.4)1) 13 412.7(6 579.1~27 344.5)1) 14.56(14.22~15.21)1) 10(9~10)1) ConA+T-MSC组 67.3(33.2~136.3)2) 168.0(103.4~272.9)2) 845.0(754.0~946.9)2) 6.45(6.14~7.23)1)2) 7(7~7)1)2) 统计值 F=151.833 F=138.682 F=106.480 H=12.522 F=12.750 P值 <0.001 <0.001 <0.001 0.002 0.002 注:与HC组比较,1)P<0.05;与ConA组比较,2)P<0.05。HC,健康对照组;Con A,模型组;Con A+T-MSC,治疗组。T-MSC,滋养层来源的间充质干细胞;Con A,刀豆蛋白A。
下载: 导出CSV
-
[1] European Association for the Study of the Liver. EASL Clinical Practice Guidelines on the management of autoimmune hepatitis[J]. J Hepatol, 2025, 83( 2): 453- 501. DOI: 10.1016/j.jhep.2025.03.017. [2] Mack C L, Adams D, Assis D N, et al. Diagnosis and management of autoimmune hepatitis in adults and children: 2019 practice guidance and guidelines from the American Association for the Study of Liver Diseases[J]. Hepatology, 2020, 72( 2): 671- 722. DOI: 10.1002/hep.31065. [3] Wang G Q, Tanaka A, Zhao H, et al. The Asian Pacific Association for the Study of the Liver clinical practice guidance: The diagnosis and management of patients with autoimmune hepatitis[J]. Hepatol Int, 2021, 15( 2): 223- 257. DOI: 10.1007/s12072-021-10170-1. [4] Gleeson D, Bornand R, Brownlee A, et al. British Society of Gastroenterology guidelines for diagnosis and management of autoimmune hepatitis[J]. Gut, 2025, 74( 9): 1364- 1409. DOI: 10.1136/gutjnl-2024-333171. [5] Korean Association for the Study of the Liver(KASL). KASL clinical practice guidelines for management of autoimmune hepatitis 2022[J]. Clin Mol Hepatol, 2023, 29( 3): 542- 592. DOI: 10.3350/cmh.2023.0087. [6] Ohira H, Takahashi A, Zeniya M, et al. Clinical practice guidelines for autoimmune hepatitis[J]. Hepatol Res, 2022, 52( 7): 571- 585. DOI: 10.1111/hepr.13776. [7] Zhou Y M, Tang R Q, Gershwin M E, et al. Autoimmune hepatitis: Pathophysiology[J]. Clin Liver Dis, 2024, 28( 1): 15- 35. DOI: 10.1016/j.cld.2023.06.003. [8] Dalekos G N, Gatselis N K. Autoimmune serology testing in clinical practice: An updated roadmap for the diagnosis of autoimmune hepatitis[J]. Eur J Intern Med, 2023, 108: 9- 17. DOI: 10.1016/j.ejim.2022.11.013. [9] Song N, Scholtemeijer M, Shah K. Mesenchymal stem cell immunomodulation: Mechanisms and therapeutic potential[J]. Trends Pharmacol Sci, 2020, 41( 9): 653- 664. DOI: 10.1016/j.tips.2020.06.009. [10] Chen Y, Chen S, Liu L Y, et al. Mesenchymal stem cells ameliorate experimental autoimmune hepatitis by activation of the programmed death 1 pathway[J]. Immunol Lett, 2014, 162( 2 Pt B): 222- 228. DOI: 10.1016/j.imlet.2014.10.021. [11] Wang H X, Liu M, Weng S Y, et al. Immune mechanisms of Concanavalin A model of autoimmune hepatitis[J]. World J Gastroenterol, 2012, 18( 2): 119- 125. DOI: 10.3748/wjg.v18.i2.119. [12] Tiegs G, Hentschel J, Wendel A. A T cell-dependent experimental liver injury in mice inducible by concanavalin A[J]. J Clin Invest, 1992, 90( 1): 196- 203. DOI: 10.1172/JCI115836. [13] Fei M M, Xie Q, Zou Y, et al. Alpha-lipoic acid protects mice against concanavalin A-induced hepatitis by modulating cytokine secretion and reducing reactive oxygen species generation[J]. Int Immunopharmacol, 2016, 35: 53- 60. DOI: 10.1016/j.intimp.2016.03.023. [14] He R, Wang L P, Zhu J L, et al. Methane-rich saline protects against concanavalin A-induced autoimmune hepatitis in mice through anti-inflammatory and anti-oxidative pathways[J]. Biochem Biophys Res Commun, 2016, 470( 1): 22- 28. DOI: 10.1016/j.bbrc.2015.12.080. [15] Kimura N, Yamagiwa S, Sugano T, et al. Possible involvement of chemokine C-C receptor 7- programmed cell death-1+ follicular helper T-cell subset in the pathogenesis of autoimmune hepatitis[J]. J Gastroenterol Hepatol, 2018, 33( 1): 298- 306. DOI: 10.1111/jgh.13844. [16] Biewenga M, Heidt S, Vergunst M, et al. B-cell activating factor and IL-21 levels predict treatment response in autoimmune hepatitis[J]. JHEP Rep, 2022, 4( 5): 100460. DOI: 10.1016/j.jhepr.2022.100460. [17] Aoki N, Kido M, Iwamoto S, et al. Dysregulated generation of follicular helper T cells in the spleen triggers fatal autoimmune hepatitis in mice[J]. Gastroenterology, 2011, 140( 4): 1322-1333.e1-5. DOI: 10.1053/j.gastro.2011.01.002. [18] Thomas-Dupont P, Remes-Troche J M, Izaguirre-Hernández I Y, et al. Elevated circulating levels of IL-21 and IL-22 define a cytokine signature profile in type 2 autoimmune hepatitis patients[J]. Ann Hepatol, 2016, 15( 4): 550- 558. DOI: 10.5604/16652681.1203152. [19] Spolski R, Leonard W J. Interleukin-21: Basic biology and implications for cancer and autoimmunity[J]. Annu Rev Immunol, 2008, 26: 57- 79. DOI: 10.1146/annurev.immunol.26.021607.090316. -

 本文二维码
计量
- 文章访问数: 10
- HTML全文浏览量: 5
- PDF下载量: 0
- 被引次数: 0




