

 PDF下载 ( 1441 KB)

肌肉减少症对慢加急性肝衰竭短期预后的影响及联合传统评分的预测增益研究
DOI: 10.12449/JCH260920
Impact of sarcopenia on short-term prognosis of acute-on-chronic liver failure and the predictive gain of combining traditional scoring systems
-
摘要:
目的 探讨肌肉减少症(肌少症)与慢加急性肝衰竭(ACLF)患者短期预后的关系,评估终末期肝病模型(MELD)、MELD-Na、MELD 3.0及中国重症乙型肝炎研究组(COSSH)-ACLF Ⅱ评分对ACLF患者90 d预后的预测价值,并分析肌少症对传统预后评分模型的预测增益价值。 方法 回顾性纳入2018年7月—2024年7月于内蒙古医科大学附属医院、呼和浩特市第二医院、呼和浩特市第一医院、内蒙古自治区人民医院住院治疗的219例ACLF患者为研究对象,依据腹部计算机体层成像测量并计算第三腰椎骨骼肌指数(L3-SMI),根据L3-SMI诊断肌少症。根据90 d预后将ACLF患者分为生存组(n=124)与死亡组(n=95)。计数资料2组间比较采用χ2检验或Fisher确切概率法。符合正态分布的计量资料2组间比较采用独立样本t检验;非正态分布的计量资料2组间比较采用Mann-Whitney U检验。采用Cox逐步向后回归法进行多因素回归分析,探究ACLF患者90 d死亡的独立危险因素。采用Kaplan-Meier法进行生存分析,组间比较采用Log-rank检验。绘制受试者操作特征曲线评估各模型的预测效能,并采用DeLong检验、Bootstrap内部验证、净重分类改善指数(NRI)及综合判别改善指数(IDI)评价肌少症的预测增益价值。 结果 多因素Cox回归分析显示,合并肌少症[风险比(HR)=3.385,95%置信区间(CI):1.722~6.657],年龄(HR=1.036,95%CI:1.017~1.056)、碱性磷酸酶(HR=1.006,95%CI:1.004~1.009)、总胆红素(HR=1.003,95%CI:1.001~1.005)、钾(HR=1.581,95%CI:1.160~2.155)、血肌酐(HR=1.015,95%CI:1.007~1.024)升高,以及凝血酶原时间(HR=1.035,95%CI:1.015~1.055)延长是ACLF患者90天死亡的独立危险因素(P值均<0.05),白蛋白(HR=0.885,95%CI:0.837~0.935)升高是ACLF患者90 d死亡的独立保护因素(P<0.05)。MELD评分、MELD-Na评分、MELD 3.0评分及COSSH-ACLF Ⅱ评分预测ACLF患者90 d预后的曲线下面积(AUC)分别为0.569、0.570、0.632和0.659,效能欠佳;其分别联合肌少症后,AUC分别提升至0.702、0.687、0.723和0.728,DeLong检验及NRI、IDI分析显示联合模型的预测效能均显著改善(P值均<0.05)。 结论 肌少症是ACLF患者90 d死亡的独立危险因素。传统评分模型对ACLF患者90 d预后的预测效能有限,联合肌少症可显著提升预测价值,可作为ACLF临床预后评估的重要补充指标。 Abstract:Objective To investigate the association between sarcopenia and short-term prognosis in patients with acute-on-chronic liver failure (ACLF), to assess the value of Model for End-Stage Liver Disease (MELD), MELD combined with serum sodium concentration (MELD-Na), MELD 3.0, and Chinese Group on the Study of Severe Hepatitis B (COSSH)-ACLF Ⅱ score in predicting the 90-day prognosis of ACLF patients, and to analyze the predictive gain of sarcopenia over traditional prognostic scoring models. Methods A retrospective study was conducted among 219 patients with ACLF who were hospitalized in The Affiliated Hospital of Inner Mongolia Medical University, No. 2 Hospital of Hohhot, Hohhot First Hospital, and Inner Mongolia People’s Hospital from July 2018 to July 2024. L3 skeletal muscle index (L3-SMI) was measured and calculated based on abdominal computed tomography images, and sarcopenia was diagnosed based on L3-SMI. According to 90-day prognosis, the patients with ACLF were divided into survival group with 124 patients and death group with 95 patients. The chi-square test or the Fisher’s exact test was used for comparison of categorical data between two groups; the independent samples t-test was used for comparison of normally distributed continuous data between two groups, and the Mann-Whitney U test was used for comparison of non-normally distributed continuous data between two groups. The multivariate Cox regression analysis (stepwise backward approach) was used to identify independent risk factors for 90-day mortality in ACLF patients. The Kaplan-Meier method was used for survival analysis, and the Log-rank test was used for comparison between groups. The receiver operating characteristic curve was plotted to evaluate the predictive performance of each model, and the DeLong test, bootstrap internal validation, net reclassification improvement (NRI), and integrated discrimination improvement (IDI) were used to assess the predictive gain of sarcopenia. Results The multivariate Cox regression analysis showed that presence of sarcopenia (hazard ratio [HR]=3.385, 95% confidence interval [CI]: 1.722 — 6.657, P<0.05), older age (HR=1.036, 95%CI: 1.017 — 1.056, P<0.05), elevated alkaline phosphatase (HR=1.006, 95%CI: 1.004 — 1.009, P<0.05), elevated total bilirubin (HR=1.003, 95%CI: 1.001 — 1.005, P<0.05), elevated potassium (HR=1.581, 95%CI: 1.160 — 2.155, P<0.05), elevated serum creatinine (HR=1.015, 95%CI: 1.007 — 1.024, P<0.05), and prolonged prothrombin time (HR=1.035, 95%CI: 1.015 — 1.055, P<0.05) were independent risk factors for 90-day mortality in ACLF patients, while elevated albumin (HR=0.885, 95%CI: 0.837 — 0.935, P<0.05) was an independent protective factor against 90-day mortality. MELD, MELD-Na, MELD 3.0, and COSSH-ACLF Ⅱ scores had an area under the ROC curve (AUC) of 0.569, 0.570, 0.632, and 0.659, respectively, for predicting the 90-day prognosis of ACLF patients, suggesting that these scores had unsatisfactory performance; after they were respectively combined with sarcopenia, the AUC was increased to 0.702, 0.687, 0.723, and 0.728, respectively. The DeLong test, NRI, and IDI analyses showed the combined models had significantly better predictive performance (all P<0.05). Conclusion Sarcopenia is an independent risk factor for 90-day mortality in patients with ACLF. Traditional scoring models have limited predictive performance for 90-day prognosis in ACLF patients, and the combination with sarcopenia significantly improves predictive value, suggesting that sarcopenia can be used as an important supplementary indicator for prognostic evaluation of ACLF in clinical practice. -
Key words:
- Acute-On-Chronic Liver Failure /
- Sarcopenia /
- Prognosis /
- Scoring Models
-
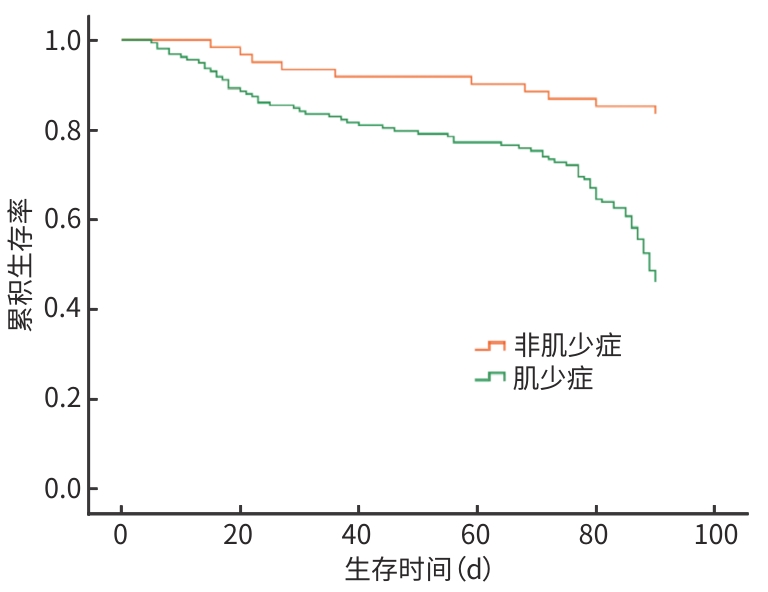
图 1 肌少症组和非肌少症组患者的生存曲线分析
Figure 1. Survival curve analysis comparing sarcopenia and non-sarcopenia cohorts
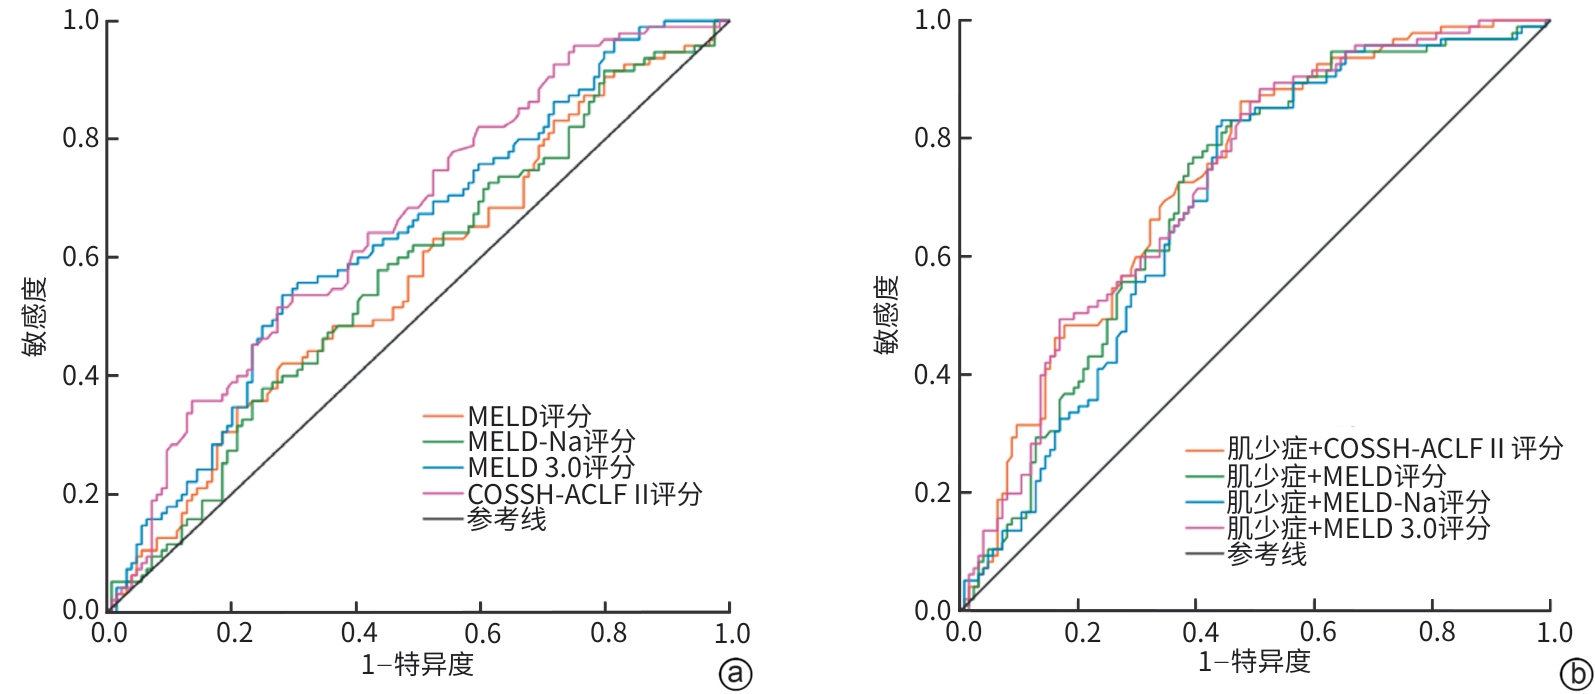
注: a,单独评分模型;b,肌少症联合评分模型。ACLF,慢加急性肝衰竭;MELD,终末期肝病模型;COSSH-ACLF,中国重症乙型肝炎研究组-慢加急性肝衰竭;ROC,受试者工作特征。
图 2 各评分模型预测 ACLF 患者 90 d 预后的 ROC 曲线
Figure 2. ROC curves of four scoring models for predicting 90-day prognosis in patients with ACLF
表 1 生存组和死亡组一般资料比较
Table 1. General clinical data in survival and death cohorts
项目 死亡组(n=95) 生存组(n=124) 统计值 P值 年龄(岁) 56.02±11.09 49.57±11.20 t=4.241 <0.001 男性[例(%)] 74(77.9) 92(74.2) χ2=0.402 0.526 肌少症[例(%)] 85(89.5) 73(58.9) χ2=25.068 <0.001 病因[例(%)] χ2=3.990 0.407 乙型肝炎 16(16.8) 25(20.2) 自身免疫性肝病 15(15.8) 16(12.9) 酒精性肝病 42(44.2) 53(42.7) 药物性肝病 2(2.1) 9(7.3) 其他原因 20(21.1) 21(16.9) 并发症[例(%)] 肝性脑病 41(43.2) 37(29.8) χ2=4.161 0.041 消化道出血 25(26.3) 25(20.2) χ2=1.156 0.282 腹水 87(91.6) 102(82.3) χ2=3.953 0.047 肝肾综合征 18(18.9) 15(12.1) χ2=1.973 0.160 腹膜炎 14(14.7) 23(18.5) χ2=0.557 0.456 感染 47(49.5) 50(40.3) χ2=1.826 0.177 评分(分) MELD评分 20.99(17.45~26.22) 20.13(15.65~23.84) Z=-1.744 0.081 MELD-Na评分 23.74(19.03~30.11) 21.73(17.82~26.76) Z=-1.778 0.075 MELD 3.0评分 25.21±7.39 21.80±7.70 t=3.305 0.001 COSSH-ACLF Ⅱ评分 7.29(6.46~8.31) 6.59(5.81~7.39) Z=-4.040 <0.001 注:MELD,终末期肝病模型;COSSH-ACLF,中国重症乙型肝炎研究组-慢加急性肝衰竭。
 下载: 导出CSV
表 2 生存组和死亡组的实验室指标比较
Table 2. Laboratory parameters in survival and death cohorts
项目 死亡组(n=95) 生存组(n=124) 统计值 P值 白细胞(×109/L) 7.16(4.69~10.09) 6.63(4.29~9.59) Z=-1.474 0.140 血红蛋白(g/L) 107.09±25.97 112.97±35.48 t=-1.414 0.159 血小板(×109/L) 82.00(47.00~123.00) 72.00(44.00~116.00) Z=-0.930 0.353 NLR 5.87(3.76~10.01) 4.18(2.63~9.38) Z=-1.993 0.046 ALT(U/L) 38.00(26.80~88.00) 36.65(23.08~65.45) Z=-1.288 0.198 AST(U/L) 96.80(47.00~182.00) 79.33(49.83~146.85) Z=-0.725 0.468 GGT(U/L) 84.00(28.00~200.00) 88.90(31.25~182.25) Z=-0.275 0.783 总胆汁酸(μmol/L) 144.10(69.70~255.10) 135.65(71.75~248.90) Z=-0.258 0.796 碱性磷酸酶(U/L) 142.38(93.45~184.80) 123.60(80.64~166.13) Z=-2.384 0.017 总蛋白(g/L) 58.74±10.56 61.34±10.53 t=-1.809 0.072 白蛋白(g/L) 25.27(22.71~29.07) 28.88(25.34~32.63) Z=-3.752 <0.001 球蛋白(g/L) 31.29±9.53 33.65±9.38 t=-1.832 0.068 总胆红素(μmol/L) 221.20(119.35~380.65) 175.85(117.43~282.40) Z=-1.856 0.063 直接胆红素(μmol/L) 114.70(64.64~255.70) 100.55(64.28~171.70) Z=-1.296 0.195 钾(mmol/L) 3.70(3.20~4.16) 3.60(3.20~4.10) Z=-1.129 0.259 钠(mmol/L) 135.77±6.41 136.32±5.91 t=-0.656 0.513 氯(mmol/L) 100.00(96.14~105.00) 101.20(97.35~105.00) Z=-0.996 0.319 钙(mmol/L) 2.10(1.98~2.39) 2.12(1.95~2.37) Z=-0.070 0.944 尿素(mmol/L) 5.64(4.00~11.10) 5.26(3.56~9.03) Z=-1.584 0.113 血肌酐(μmol/L) 76.44(58.80~94.50) 65.74(50.35~88.28) Z=-2.321 0.020 尿酸(μmol/L) 288.00(183.20~413.50) 269.00(186.48~348.75) Z=-0.580 0.562 凝血酶原时间(s) 21.10(18.40~25.00) 20.25(18.30~23.90) Z=-0.749 0.454 INR 1.83(1.60~2.15) 1.78(1.60~2.10) Z=-0.564 0.573 活化部分凝血活酶时间(s) 40.40(34.10~47.60) 41.30(33.98~49.68) Z=-0.757 0.449 纤维蛋白原(g/L) 1.48(1.13~1.98) 1.35(1.01~1.89) Z=-1.012 0.311 凝血酶时间(s) 19.90(18.40~22.00) 20.80(18.23~23.08) Z=-0.980 0.327 注:NLR,中性粒细胞与淋巴细胞比值;ALT,丙氨酸氨基转移酶;AST,天冬氨酸氨基转移酶;GGT,γ-谷氨酰转移酶;INR,国际标准化比值。
下载: 导出CSV
表 3 ACLF患者90 d预后的Cox回归分析
Table 3. Cox regression analysis of 90-day prognosis in ACLF patients
变量 单因素分析 多因素分析 HR 95%CI P值 HR 95%CI P值 性别 1.143 0.704~1.855 0.590 年龄(岁) 1.035 1.018~1.053 <0.001 1.036 1.017~1.056 <0.001 肌少症 4.118 2.137~7.936 <0.001 3.385 1.722~6.657 <0.001 肝性脑病 1.606 1.070~2.410 0.022 消化道出血 1.303 0.825~2.057 0.257 腹水 1.878 0.910~3.876 0.088 肝肾综合征 1.634 0.978~2.730 0.061 腹膜炎 0.821 0.465~1.448 0.496 感染 1.379 0.922~2.062 0.118 白细胞(×109/L) 1.029 0.997~1.062 0.079 血红蛋白(g/L) 0.996 0.990~1.002 0.107 血小板(×109/L) 1.002 0.999~1.006 0.298 NLR 1.026 1.003~1.049 0.027 ALT(U/L) 1.000 1.000~1.000 0.830 AST(U/L) 1.000 0.999~1.001 0.838 GGT(U/L) 1.000 0.999~1.001 0.541 血清总胆汁酸(μmol/L) 1.000 0.999~1.002 0.909 碱性磷酸酶(U/L) 1.004 1.001~1.007 0.002 1.006 1.004~1.009 <0.001 总蛋白(g/L) 0.982 0.964~1.001 0.060 白蛋白(g/L) 0.938 0.905~0.973 <0.001 0.885 0.837~0.935 <0.001 球蛋白(g/L) 0.979 0.958~1.001 0.056 总胆红素(μmol/L) 1.001 1.000~1.003 0.023 1.003 1.001~1.005 0.009 直接胆红素(μmol/L) 1.002 1.000~1.004 0.025 钾(mmol/L) 1.389 1.039~1.857 0.026 1.581 1.160~2.155 0.004 钠(mmol/L) 0.989 0.955~1.023 0.524 氯(mmol/L) 0.988 0.957~1.019 0.436 钙(mmol/L) 1.181 0.600~2.322 0.631 尿素(mmol/L) 0.999 0.993~1.005 0.673 血肌酐(μmol/L) 1.006 1.003~1.009 <0.001 1.015 1.007~1.024 <0.001 尿酸(μmol/L) 1.001 1.000~1.002 0.131 凝血酶原时间(s) 1.010 0.999~1.021 0.084 1.035 1.015~1.055 <0.001 INR 1.095 0.970~1.236 0.142 活化部分凝血活酶时间(s) 0.995 0.980~1.011 0.546 纤维蛋白原(g/L) 0.971 0.861~1.094 0.626 凝血酶时间(s) 0.989 0.940~1.040 0.661 注:ACLF,慢加急性肝衰竭;NLR,中性粒细胞与淋巴细胞比值;ALT,丙氨酸氨基转移酶;AST,天冬氨酸氨基转移酶;GGT,γ-谷氨酰转移酶;INR,国际标准化比值;HR,风险比;CI,置信区间。计数资料赋值:性别(男=1,女=0);肌少症(有=1,无=0);肝性脑病(有=1,无=0);消化道出血(有=1,无=0);腹水(有=1,无=0);肝肾综合征(有=1,无=0);腹膜炎(有=1,无=0);感染(有=1,无=0)。
下载: 导出CSV
表 4 4种评分模型对ACLF患者90 d预后的预测效能
Table 4. Predictive performance of four scoring models for 90-day prognosis in patients with ACLF
指标 AUC 95%CI 最佳截断值(分) 敏感度(%) 特异度(%) P值 MELD评分 0.569 0.492~0.645 23.335 42.1 71.8 0.081 MELD-Na评分 0.570 0.494~0.646 22.560 57.9 56.5 0.075 MELD 3.0评分 0.632 0.558~0.705 24.535 53.7 71.8 0.001 COSSH-ACLF Ⅱ评分 0.659 0.588~0.731 7.275 51.6 72.6 <0.001 注:AUC,曲线下面积;CI,置信区间;ACLF,慢加急性肝衰竭;MELD,终末期肝病模型;COSSH-ACLF,中国重症乙型肝炎研究组-慢加急性肝衰竭。
下载: 导出CSV
表 5 肌少症联合4种评分模型对ACLF患者90 d预后的预测效能
Table 5. Predictive performance of sarcopenia combined with four scoring models for 90-day prognosis in patients with ACLF
指标 AUC 95%CI 最佳截断值(分) 敏感度(%) 特异度(%) P值 肌少症+MELD评分 0.702 0.633~0.771 0.485 76.8 60.5 <0.001 肌少症+MELD-Na评分 0.687 0.617~0.757 0.491 83.2 55.6 <0.001 肌少症+MELD 3.0评分 0.723 0.657~0.790 0.395 88.4 49.2 <0.001 肌少症+COSSH-ACLF Ⅱ评分 0.728 0.662~0.794 0.407 86.3 52.4 <0.001 注:AUC,曲线下面积;CI,置信区间;ACLF,慢加急性肝衰竭;MELD,终末期肝病模型;COSSH-ACLF,中国重症乙型肝炎研究组-慢加急性肝衰竭。
下载: 导出CSV
表 6 肌少症联合传统评分模型对ACLF患者90 d预后的预测增益效能
Table 6. Predictive gain of sarcopenia combined with traditional scoring models for 90-day prognosis in patients with ACLF
指标 DeLong检验 Bootstrap内部验证 AUC差值(95%CI) P值 校正后AUC差值
(95%CI)分类NRI(95%CI) IDI(95%CI) 肌少症+MELD评分 0.133(0.066~0.199) <0.001 0.137(0.070~0.213) 0.303(0.202~0.404) 0.115(0.077~0.154) 肌少症+MELD-Na评分 0.117(0.055~0.179) <0.001 0.122(0.059~0.179) 0.303(0.202~0.404) 0.110(0.072~0.147) 肌少症+MELD 3.0评分 0.091(0.031~0.152) 0.003 0.091(0.032~0.148) 0.210(0.095~0.326) 0.105(0.069~0.140) 肌少症+COSSH-ACLF Ⅱ评分 0.069 (0.015~0.123) 0.013 0.067(0.020~0.118) 0.148(0.034~0.261) 0.087(0.053~0.121) 注:NRI,净重分类改善指数;IDI,综合判别改善指数;AUC,曲线下面积;CI,置信区间;ACLF,慢加急性肝衰竭;MELD,终末期肝病模型;COSSH-ACLF,中国重症乙型肝炎研究组-慢加急性肝衰竭。
下载: 导出CSV
-
[1] Shang Dabao, Xiang Xiaogang. Advances in the pathogenesis and treatment of acute-on-chronic liver failure[J]. J Clin Hepatol, 2021, 37( 4): 765- 769. DOI: 10.3969/j.issn.1001-5256.2021.04.005.尚大宝, 项晓刚. 慢加急性肝衰竭的发病机制和治疗进展[J]. 临床肝胆病杂志, 2021, 37( 4): 765- 769. DOI: 10.3969/j.issn.1001-5256.2021.04.005. [2] Br V K, Sarin S K. Acute-on-chronic liver failure: Terminology, mechanisms and management[J]. Clin Mol Hepatol, 2023, 29( 3): 670- 689. DOI: 10.3350/cmh.2022.0103. [3] Coletta G, Phillips S M. An elusive consensus definition of sarcopenia impedes research and clinical treatment: A narrative review[J]. Ageing Res Rev, 2023, 86: 101883. DOI: 10.1016/j.arr.2023.101883. [4] Bunchorntavakul C, Reddy K R. Review article: Malnutrition/sarcopenia and frailty in patients with cirrhosis[J]. Aliment Pharmacol Ther, 2020, 51( 1): 64- 77. DOI: 10.1111/apt.15571. [5] Beumer B R, van Vugt J L A, Sapisochin G, et al. Impact of muscle mass on survival of patients with hepatocellular carcinoma after liver transplantation beyond the Milan criteria[J]. J Cachexia Sarcopenia Muscle, 2022, 13( 5): 2373- 2382. DOI: 10.1002/jcsm.13053. [6] Barnhill M S, Carey E J. Compartmentalizing risk with sarcopenic obesity[J]. Liver Transplant, 2023, 29( 5): 463- 464. DOI: 10.1097/lvt.0000000000000061. [7] Lu Xuemei, Yang Yuhang, Wang Kaiti, et al. Research progress on sarcopenia in the field of liver transplantation[J]. Chin J Dig Surg, 2025, 24( 11): 1501- 1506. DOI: 10.3760/cma.j.cn115610-20250818-00539.鲁雪梅, 杨宇航, 王恺悌, 等. 肌少症在肝移植领域的研究进展[J]. 中华消化外科杂志, 2025, 24( 11): 1501- 1506. DOI: 10.3760/cma.j.cn115610-20250818-00539. [8] Sarin S K, Choudhury A, Sharma M K, et al. Acute-on-chronic liver failure: Consensus recommendations of the Asian Pacific Association for the Study of the Liver(APASL): An update[J]. Hepatol Int, 2019, 13( 4): 353- 390. DOI: 10.1007/s12072-019-09946-3. [9] Chen L K, Woo J, Assantachai P, et al. Asian working group for sarcopenia: 2019 consensus update on sarcopenia diagnosis and treatment[J]. J Am Med Dir Assoc, 2020, 21( 3): 300- 307. DOI: 10.1016/j.jamda.2019.12.012. [10] Kong M, Geng N, Zhou Y, et al. Defining reference values for low skeletal muscle index at the L3 vertebra level based on computed tomography in healthy adults: A multicentre study[J]. Clin Nutr, 2022, 41( 2): 396- 404. DOI: 10.1016/j.clnu.2021.12.003. [11] Sayer A A, Cruz-Jentoft A. Sarcopenia definition, diagnosis and treatment: Consensus is growing[J]. Age Ageing, 2022, 51( 10): afac220. DOI: 10.1093/ageing/afac220. [12] Tantai X X, Liu Y, Yeo Y H, et al. Effect of sarcopenia on survival in patients with cirrhosis: A meta-analysis[J]. J Hepatol, 2022, 76( 3): 588- 599. DOI: 10.1016/j.jhep.2021.11.006. [13] Ma L Y, Liu S Q, Xing H, et al. Research progress on short-term prognosis of acute-on-chronic liver failure[J]. Expert Rev Gastroenterol Hepatol, 2023, 17( 1): 45- 57. DOI: 10.1080/17474124.2023.2165063. [14] Li T Z, Xu M M, Kong M, et al. Use of skeletal muscle index as a predictor of short-term mortality in patients with acute-on-chronic liver failure[J]. Sci Rep, 2021, 11( 1): 12593. DOI: 10.1038/s41598-021-92087-1. [15] Zeng F, Jiang W, Chang X J, et al. Sarcopenia is associated with short- and long-term mortality in patients with acute-on-chronic liver failure[J]. J Cachexia Sarcopenia Muscle, 2024, 15( 4): 1473- 1482. DOI: 10.1002/jcsm.13501. [16] Geng N, Kong M, Zhang J T, et al. Association of myosteatosis with short-term outcomes in patients with acute-on-chronic liver failure[J]. Sci Rep, 2024, 14( 1): 13609. DOI: 10.1038/s41598-024-64420-x. [17] Allen S L, Quinlan J I, Dhaliwal A, et al. Sarcopenia in chronic liver disease: Mechanisms and countermeasures[J]. Am J Physiol Gastrointest Liver Physiol, 2021, 320( 3): G241- G257. DOI: 10.1152/ajpgi.00373.2020. [18] Cox M C, Booth M, Ghita G, et al. The impact of sarcopenia and acute muscle mass loss on long-term outcomes in critically ill patients with intra-abdominal sepsis[J]. J Cachexia Sarcopenia Muscle, 2021, 12( 5): 1203- 1213. DOI: 10.1002/jcsm.12752. [19] Mangana del Rio T, Sacleux S C, Vionnet J, et al. Body composition and short-term mortality in patients critically ill with acute-on-chronic liver failure[J]. JHEP Rep, 2023, 5( 8): 100758. DOI: 10.1016/j.jhepr.2023.100758. [20] Trebicka J, Hernaez R, Shawcross D L, et al. Recent advances in the prevention and treatment of decompensated cirrhosis and acute-on-chronic liver failure(ACLF) and the role of biomarkers[J]. Gut, 2024, 73( 6): 1015- 1024. DOI: 10.1136/gutjnl-2023-330584. [21] Huang J J, Cai M, He X. Serum potassium levels and prognosis in HBV-associated decompensated cirrhosis[J]. J Clin Lab Anal, 2021, 35( 6): e23775. DOI: 10.1002/jcla.23775. [22] Wei Guizhi, Fan Feifei, Wang Yutong. Analysis of the causes and prognostic factors of acute liver failure and acute-on-chronic liver failure[J]. Clin Misdiagnosis Mistherapy, 2026, 39( 5): 23- 29. DOI: 10.3969/j.issn.1002-3429.2026.05.005.魏桂枝, 樊菲菲, 王玉同. 急性肝功能衰竭及慢加急性肝功能衰竭的病因及预后影响因素分析[J]. 临床误诊误治, 2026, 39( 5): 23- 29. DOI: 10.3969/j.issn.1002-3429.2026.05.005. [23] Shi S, Yang Y F, Liu Y L, et al. Development and validation of a machine learning model to predict prognosis in liver failure patients treated with non-bioartificial liver support system[J]. Front Med, 2024, 11: 1368899. DOI: 10.3389/fmed.2024.1368899. [24] Chen Jiaoyan, Chen Bin, Cao Dongrong, et al. Risk factors for liver failure-related death in chronic hepatitis B patients[J]. Chin Hepatol, 2021, 26( 9): 994- 997. DOI: 10.14000/j.cnki.issn.1008-1704.2021.09.014.陈姣艳, 陈斌, 曹冬容, 等. 慢性乙型肝炎并发肝衰竭死亡危险因素的研究[J]. 肝脏, 2021, 26( 9): 994- 997. DOI: 10.14000/j.cnki.issn.1008-1704.2021.09.014. [25] Balabanova L, Bondarev G, Seitkalieva A, et al. Insights into alkaline phosphatase anti-inflammatory mechanisms[J]. Biomedicines, 2024, 12( 11): 2502. DOI: 10.3390/biomedicines12112502. [26] Engelmann C, Adebayo D, Oria M, et al. Recombinant alkaline phosphatase prevents acute on chronic liver failure[J]. Sci Rep, 2020, 10( 1): 389. DOI: 10.1038/s41598-019-57284-z. [27] Le Couteur D G, Ngu M C, Hunt N J, et al. Liver, ageing and disease[J]. Nat Rev Gastroenterol Hepatol, 2025, 22( 10): 680- 695. DOI: 10.1038/s41575-025-01099-z. [28] Jiang W Y, Hu Y C, Sun Y, et al. Prevalence and short-term outcome of acute kidney injury in patients with acute-on-chronic liver failure: A meta-analysis[J]. J Viral Hepat, 2020, 27( 8): 810- 817. DOI: 10.1111/jvh.13287. -

 本文二维码
计量
- 文章访问数: 13
- HTML全文浏览量: 9
- PDF下载量: 0
- 被引次数: 0




