

 PDF下载 ( 11996 KB)

家族性ⅣA型遗传性血色病1例报告
DOI: 10.12449/JCH260922
伦理学声明:本例报告已获得患者及家属知情同意。
利益冲突声明:本文不存在任何利益冲突。
作者贡献声明:范艳玲负责文章初稿的撰写与数据整理;李艳萌、黄坚负责基因检测分析与方法学验证;武丽娜、武祯和欧晓娟负责病例的临床诊断、家系追踪与资料收集;张伟负责全文的核验、修改与最终审定。
-
摘要: 遗传性血色病(HH)是一类因铁代谢相关基因突变导致铁过载的遗传性疾病。ⅣA型HH(即经典型膜铁转运蛋白病)由SLC40A1基因功能缺失性变异引起,其临床表现为血清铁蛋白(SF)水平显著升高、转铁蛋白饱和度正常或降低以及脾脏铁沉积明显。本文报道1例ⅣA型HH患者,临床表现为无症状的SF水平显著增高,磁共振成像提示脾脏铁过载明显重于肝脏铁过载,经皮肝脏活组织检查提示轻度脂肪肝、Kupffer细胞铁沉积,基因变异分析检出SLC40A1 c.485_487del(p.Val162del)杂合变异。对家系成员进行筛查,其母亲亦携带相同变异,且伴有肝、脾铁过载表现,进一步证实该变异的致病性。本案例提示,ⅣA型HH起病隐匿,易被误诊;对于无法解释的SF水平持续升高者,即使合并其他肝病,也应积极进行HH基因检测,以实现早期诊断与干预。
-
关键词:
- 遗传性疾病, 先天性 /
- 膜铁转运蛋白病 /
- 铁过载
Abstract: Hereditary hemochromatosis (HH) is a hereditary disease characterized by iron overload resulting from mutations in genes involved in iron metabolism. Type ⅣA HH, also known as classical ferroportin disease, is caused by loss-of-function mutations in the SLC40A1 gene and has the clinical manifestations of a significant increase in serum ferritin, normal or low transferrin saturation, and marked iron deposition in the spleen. This article reports a case of type ⅣA HH with a significant asymptomatic increase in serum ferritin. Magnetic resonance imaging showed that the severity of iron overload in the spleen was significantly higher than that in the liver; liver biopsy showed mild fatty liver disease and iron deposition in Kupffer cells; gene variation analysis identified a heterozygous mutation in SLC40A1 c.485_487del (p.Val162del). Screening of family members showed that the proband’s mother carried the same variation and had the manifestation of iron overload in the liver and spleen, which further confirmed the pathogenicity of this variation. This case highlights that type ⅣA HH often has an insidious onset and is frequently misdiagnosed. For patients with an unexplained persistent increase in serum ferritin, active genetic testing for HH should be considered, even in the presence of concurrent liver diseases, in order to realize early diagnosis and intervention.-
Key words:
- Genetic Diseases, Inborn /
- Ferroportin Disease /
- Iron Overload
-
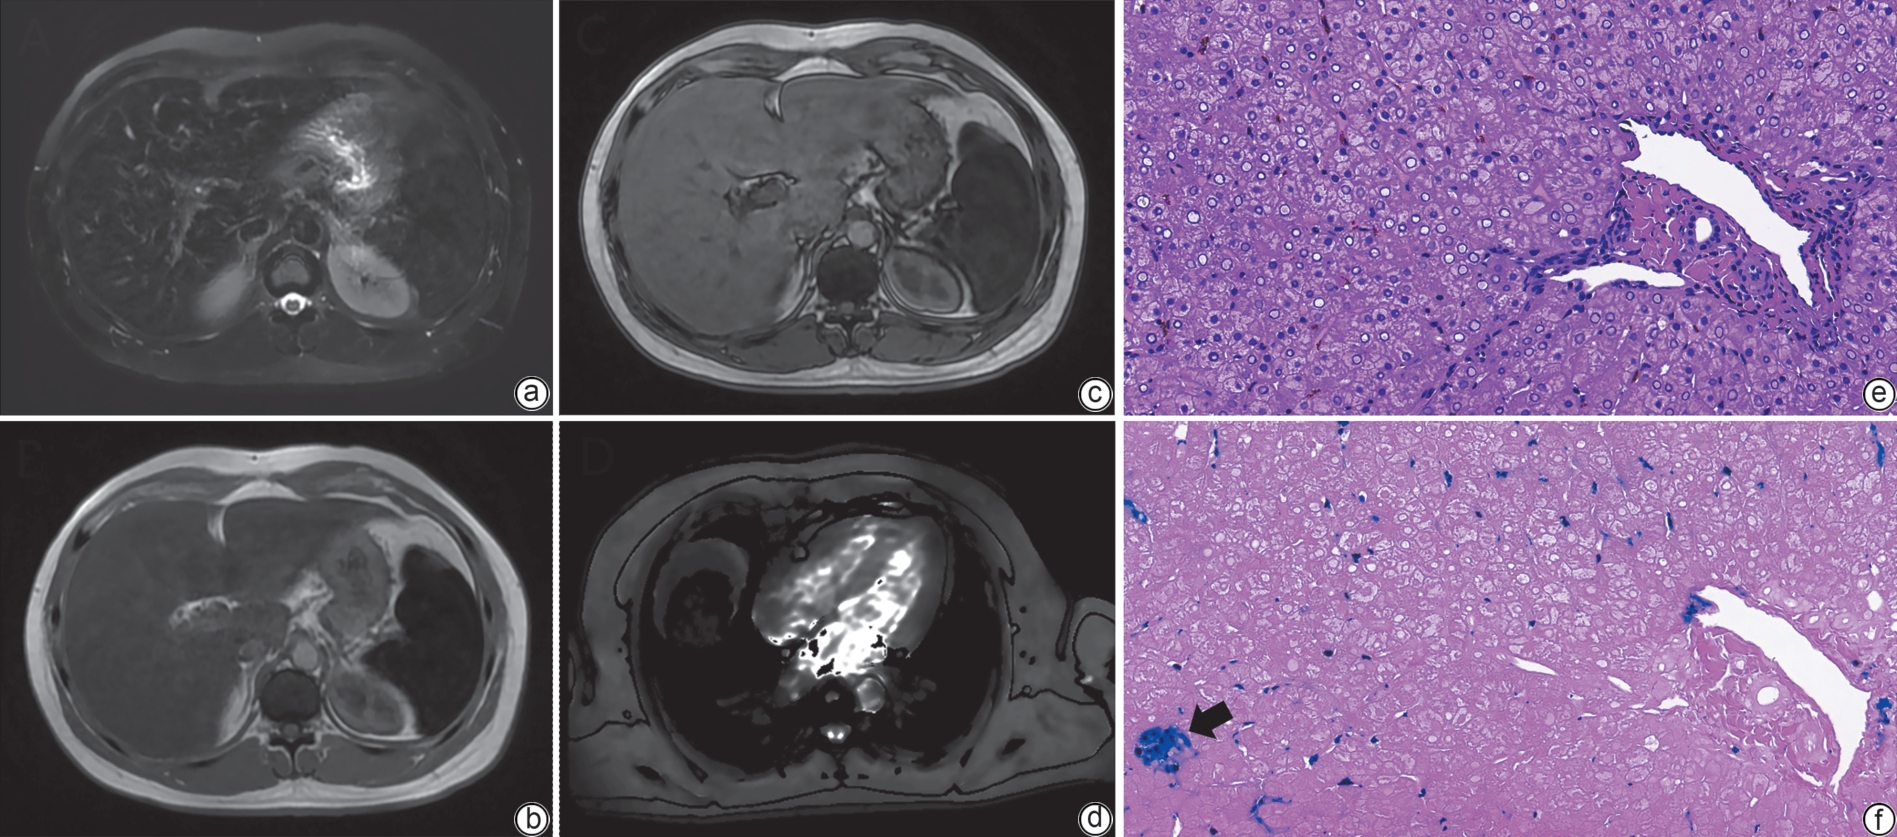
注: a~c,腹部核磁:a,肝、脾实质信号弥漫性减低,明显低于椎旁肌;T1加权像双回波显示肝、脾同相位(b)信号低于反相位(c),提示肝脾铁过载。d,心脏核磁:乳头肌水平前壁T2*值约为16.5 ms,心尖部游离壁心肌T2*值为12.5~16.4 ms。e,小叶结构保留,汇管区见少量淋巴细胞浸润;肝细胞大泡性脂肪变性,范围约5%(苏木精-伊红染色,×400);f,肝细胞内可见色素沉积,少量Kupffer细胞内可见含铁血黄素沉积(黑色箭头所示)(普鲁士蓝染色,×400)。
图 1 腹部、心脏核磁及肝穿刺病理结果
Figure 1. Abdominal, cardial MRI and histopathological findings of liver biopsy specimens
-
[1] Adams P C, Jeffrey G, Ryan J. Haemochromatosis[J]. Lancet, 2023, 401( 10390): 1811- 1821. DOI: 10.1016/S0140-6736(23)00287-8. [2] Camaschella C, Poggiali E. Rare types of genetic hemochromatosis[J]. Acta Haematol, 2009, 122( 2-3): 140- 145. DOI: 10.1159/000243798. [3] Kowdley K V, Brown K E, Ahn J, et al. ACG clinical guideline: Hereditary hemochromatosis[J]. Am J Gastroenterol, 2019, 114( 8): 1202- 1218. DOI: 10.14309/ajg.0000000000000315. [4] Zhang W, Xu A J, Li Y M, et al. A novel SLC40A1 p.Y333H mutation with gain of function of ferroportin: A recurrent cause of haemochromatosis in China[J]. Liver Int, 2019, 39( 6): 1120- 1127. DOI: 10.1111/liv.14013. [5] Chinese Society of Hepatology, Chinese Medical Association. Chinese guidelines for the diagnosis and treatment of hereditary hemochromatosis[J]. Chin J Hepatol, 2024, 32( 9): 787- 798. DOI: 10.3760/cma.j.cn501113-20240712-00319.中华医学会肝病学分会. 中国遗传性血色病诊疗指南[J]. 中华肝脏病杂志, 2024, 32( 9): 787- 798. DOI: 10.3760/cma.j.cn501113-20240712-00319. [6] Hao Kunyan, Wang Yong, Yu Yuecheng. An excerpt of the EASL clinical practice guidelines on haemochromatosis[J]. J Clin Hepatol, 2022, 38( 9): 1999- 2004. DOI: 10.3969/j.issn.1001-5256.2022.09.011.郝坤艳, 汪勇, 于乐成.《2022年欧洲肝病学会血色病临床实践指南》摘译[J]. 临床肝胆病杂志, 2022, 38( 9): 1999- 2004. DOI: 10.3969/j.issn.1001-5256.2022.09.011. [7] Lv T X, Zhang W, Xu A J, et al. Non-HFE mutations in haemochromatosis in China: Combination of heterozygous mutations involving HJV signal peptide variants[J]. J Med Genet, 2018, 55( 10): 650- 660. DOI: 10.1136/jmedgenet-2018-105348. [8] Mayr R, Janecke A R, Schranz M, et al. Ferroportin disease: A systematic meta-analysis of clinical and molecular findings[J]. J Hepatol, 2010, 53( 5): 941- 949. DOI: 10.1016/j.jhep.2010.05.016. [9] Zhu Chengyu, Chen Qi, Feng Zhongxin. Hereditary hemochromatosis caused by mutation in the SLC40 A1 gene: A case report[J]. J Clin Hepatol, 2021, 37( 5): 1180- 1182. DOI: 10.3969/j.issn.1001-5256.2021.05.041.朱承谕, 陈琦, 封忠昕. SLC40 A1基因突变致遗传性血色病1例报告[J]. 临床肝胆病杂志, 2021, 37( 5): 1180- 1182. DOI: 10.3969/j.issn.1001-5256.2021.05.041. [10] Girelli D, Busti F, Brissot P, et al. Hemochromatosis classification: Update and recommendations by the BIOIRON Society[J]. Blood, 2022, 139( 20): 3018- 3029. DOI: 10.1182/blood.2021011338. [11] Uguen K, Ka C, Collod-Béroud G, et al. The spectra of disease-causing mutations in the ferroportin 1(SLC40A1) encoding gene and related iron overload phenotypes(hemochromatosis type 4 and ferroportin disease)[J]. Hum Mutat, 2023, 2023: 5162256. DOI: 10.1155/2023/5162256. [12] Czaja A J. Review article: Iron disturbances in chronic liver diseases other than haemochromatosis- pathogenic, prognostic, and therapeutic implications[J]. Aliment Pharmacol Ther, 2019, 49( 6): 681- 701. DOI: 10.1111/apt.15173. [13] Li Guangming, Fan Jiangao. Research progress in role of iron overload in non-alcoholic fatty liver disease[J]. J Clin Hepatol, 2013, 29( 12): 897- 900. DOI: 10.3969/j.issn.1001-5256.2013.12.006.李光明, 范建高. 铁超载在非酒精性脂肪性肝病中的作用[J]. 临床肝胆病杂志, 2013, 29( 12): 897- 900. DOI: 10.3969/j.issn.1001-5256.2013.12.006. [14] Pietrangelo A. Ferroportin disease: Pathogenesis, diagnosis and treatment[J]. Haematologica, 2017, 102( 12): 1972- 1984. DOI: 10.3324/haematol.2017.170720. -

 下载:
 本文二维码
图(2)
计量
- 文章访问数: 13
- HTML全文浏览量: 5
- PDF下载量: 0
- 被引次数: 0




